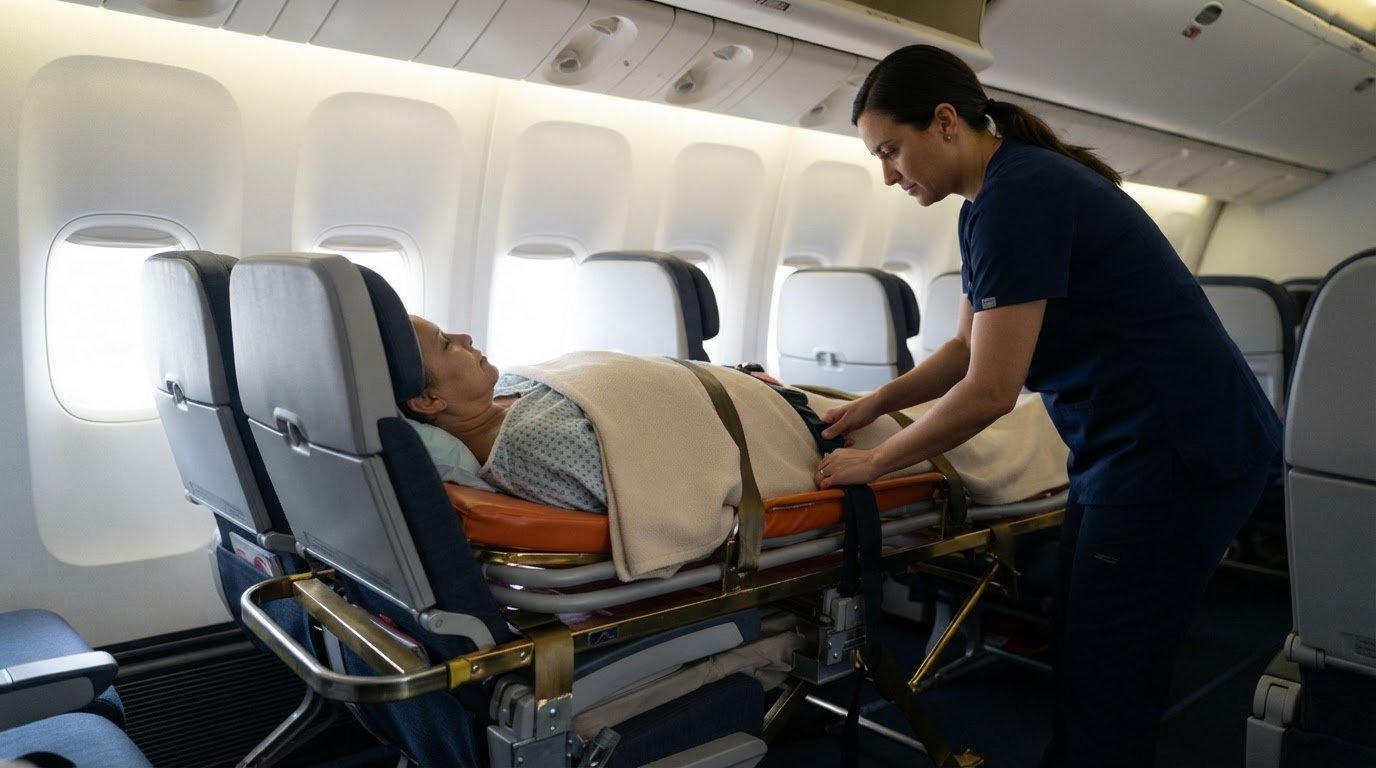
Hospital Patient Transfer Escorts and Readmission Risk
Hospital discharges and inter-facility transfers are among the points where patient care is most likely to break down. When a patient moves from one clinical setting to another, medication changes, pending results, and symptom instructions can be lost in the handoff. Readmission is one measurable result of these gaps. This article explains how hospitals use a hospital patient transfer medical escort to reduce readmission risk, what a registered nurse (RN) escort does during travel and at arrival, and how these services fit into domestic and international transfer planning.
Table of Contents
Quick Takeaways
Key Insight | Explanation |
|---|---|
Readmission risk concentrates at the handoff | Information lost between the discharging unit and the receiving team is a recognized contributor to avoidable returns, so the transfer itself needs a documented plan. |
Escorted travel suits medically stable patients | An RN escort is appropriate for patients who are stable for travel but still need observation and supervision, not for patients who require critical care in transit. |
The escort monitors and records changes in transit | An RN can observe breathing, oxygen needs, mobility, and symptoms during the journey and document timed findings for the receiving team. |
Written handoffs carry more weight than verbal summaries | A single printed medication list, pending results list, and contact sheet reduces ambiguity at arrival. |
Confirm the accepting clinician before departure | A transfer that arrives without an accepting physician or a confirmed bed shifts risk to the patient and the family. |
Match the transfer method to the level of care | A dedicated air ambulance serves higher acuity needs, while RN-accompanied commercial travel serves patients who need supervision without that level of care. A free quote is available by calling (210)-901-5226. |
Why Readmissions Occur During Patient Transfers
Every transfer creates a point where clinical information must move from one team to another. When that movement is incomplete, the receiving clinician may not know which symptoms to watch, which medications were changed, or which results are still pending. Readmission is the outcome most often tracked when these gaps lead to a return to acute care.

Gaps at the handoff
A handoff is most vulnerable when it relies on verbal summaries. A discharge summary may be completed after the patient has already left the unit, and a telephone report may omit details the sending nurse considered routine. In practice, the receiving facility often learns about an oxygen requirement, a wound dressing schedule, or a recent fall only after the patient arrives.
Care transition research has addressed this problem directly. A 2023 article in Cureus on implementing care transition teams presents coordinated transition support as a means to mitigate hospital readmissions and improve patient outcomes. The article reinforces a practical point: the handoff is a clinical task, not only an administrative one.
Medication and follow-up discrepancies
Medication changes and unclear follow-up instructions are frequent sources of confusion after transfer. A patient may arrive with a changed anticoagulant dose, a new antibiotic that does not appear in the receiving facility's record, or a follow-up appointment that was never booked. Each of these problems can delay recognition of deterioration.
Transitional care research points in a consistent direction. A 2021 article in BMJ Open reported that transitional care interventions reduce readmission rates among older medical patients, although the size of the effect varies with the timing of outcome assessment. For hospital planners, this means the transition deserves structure in its own right, not only the clinical care that precedes it.
How an RN Escort Changes Transit
A registered nurse escort addresses the gap between a discharge plan written on paper and the conditions the patient experiences during travel. The escort does not replace the receiving team. The escort's role is to observe, document, and communicate, so that clinicians at the destination receive accurate information about the patient's condition at the time of arrival.
Clinical observation during transit
During a commercial flight, the escort monitors comfort, breathing, skin condition, hydration, and mobility, and watches for signs that the patient's condition is changing. Oxygen use, mobility limits, and fatigue can shift within hours of leaving a facility. A nurse who is present can recognize these changes early and act within the scope of the escort plan.
Observation is useful only when it is recorded. Escort notes should show times, observed findings, interventions, and the patient's responses. These entries become part of the handoff packet and give the receiving team a timeline rather than a single summary.
A transfer record is only as useful as its timeline. Entries that show when a finding was observed allow the receiving clinician to judge whether a change is new or long-standing.
Documentation for the receiving team
The handoff packet should contain the discharge medication list, the most recent set of vital signs, pending laboratory or imaging results, allergies, code status, and the names and telephone numbers of responsible clinicians at both ends. The packet is most effective when it is reviewed with the patient and family before departure, so that everyone refers to the same list.
Pro tip: Ask the sending team to flag every medication that changed during the admission, and place those changes on the first page of the packet. A receiving clinician who sees the change immediately is less likely to miss it during the first medication pass.
Clear documentation also supports the patient and family. When they hold a copy of the same list, they can ask targeted questions at the receiving facility and recognize symptoms that warrant a call to the clinical team.
Hospital-to-Hospital Transfers
Hospital-to-hospital transfers occur when a patient needs care that the sending facility cannot provide, such as a specialty consultation, a procedure, or a bed in a unit with different capabilities. These transfers often cover distances that require air travel, and they carry a high risk of information loss because two organizations must align on one plan.

Confirming the accepting clinician
A transfer should not be scheduled until an accepting physician has agreed to the admission and the receiving unit is prepared. Escorts who arrive with a patient and no accepting clinician face delays at the door, and the patient may wait while the receiving team reviews the chart. Confirming acceptance, bed assignment, and the expected arrival time before booking removes much of this uncertainty.
Aligning the clinical plan with the destination
The receiving hospital may use different order sets, medication formularies, or monitoring routines. A plan written for one facility can conflict with another. The escort packet should therefore state which orders are active, which are pending, and which the receiving team must review on arrival.
Planning considerations for this type of transfer are covered in more detail in our guide to hospital-to-hospital medical escort planning. The guide addresses coordination steps that apply to domestic transfers of all distances.
Discharge Home and Door-to-Door Transitions
Some patients return home after an admission but still need supervision during travel. This applies to patients who are medically stable yet not ready to manage a long journey alone. A door-to-door medical escort covers the path from the discharging unit to the patient's home or next care setting, which closes a gap that many discharge plans leave open.
Discharge timing and escort scope
Escorts should be booked against a confirmed discharge time, not a provisional one. When discharge moves by several hours, the escort schedule, the flight, and the patient's medication timing all require adjustment. Confirming the discharge order, the discharge summary, and the medication supply before the escort arrives prevents avoidable delays.
Coordinating arrival at home
Arrival at home is a separate handoff. The patient may need equipment, prescriptions filled at a pharmacy, a caregiver present, and a plan for the first day at home. A discharge plan that ends at the hospital door leaves the family to solve these problems alone.
Pro tip: Before booking, confirm that the home has a working telephone, that a caregiver will be present on arrival, and that prescriptions are in hand. These three checks address several of the practical causes of a same-day return to the hospital.
The hospital discharge process is discussed in more detail in our resource on hospital patient discharge air transport with RN escorts, which outlines how discharge timing and escort scope are coordinated.
Nursing Home and Skilled Nursing Returns
Transfers between hospitals and nursing homes or skilled nursing facilities involve a different set of risks. The receiving facility may have limited overnight nursing coverage, different medication administration systems, and staff who did not see the patient during the acute episode. A nursing home medical escort helps close these gaps by providing an RN who can communicate directly with the facility's nursing team at arrival.

Receiving facility handoffs
At arrival, the escort should speak with the charge nurse or the nurse who will assume care, rather than leaving the packet at the front desk. A brief verbal handoff, paired with a written list, allows the facility to confirm the medication schedule, the diet order, and any monitoring thresholds. A clear summary places the receiving nurses in a better position to notice early changes.
Roles for families and case managers
Families and case managers often coordinate a return from a distance. Their role is to confirm the receiving facility's acceptance, the expected arrival time, and any equipment or therapy orders that must be in place. A case manager who sends these details in writing before the transfer date reduces the number of follow-up calls the facility must answer on the day of arrival.
For facilities that want to review the scope of this service, our page on nursing home medical escort RN-led facility transfers describes how these returns are typically organized.
Domestic and International Transfers
The same handoff principles apply to domestic and international transfers, but the planning window is longer and the documentation burden is greater. Each additional border, time zone, or language change adds steps that the receiving team must understand. Planning should begin when a transfer is first considered, not on the day of travel.
Domestic transfers
Domestic transfers often involve familiar regulatory frameworks and shorter travel times. The main risk is incomplete information about the receiving facility's capacity. Confirming bed type, monitoring availability, and the accepting unit before the flight keeps the plan on schedule.
International repatriation planning
International repatriation requires documented consent, a verified accepting facility abroad, and records that clinicians in the receiving country can read. Medication names may differ across countries, and dosage units can vary. A structured checklist covering these elements reduces the chance that a critical item is missed. Our international medical escort checklist outlines these steps in sequence.
Choosing the Right Transfer Option
The appropriate transfer method depends on clinical stability, travel distance, and the level of monitoring required during travel. The comparison below reviews three options that hospitals and case managers commonly evaluate when planning a transfer.
Transfer Option | Best Suited For | Key Considerations |
|---|---|---|
RN-escorted commercial flight | Medically stable patients who need supervision, observation, and documentation during travel | Requires a stable patient, a confirmed accepting facility, and a complete handoff packet |
Dedicated air ambulance | Patients whose condition requires continuous, higher-level medical care during transport | Designed for higher acuity needs, with a cost substantially above an RN-accompanied commercial flight |
Unescorted commercial travel with written instructions | Independent patients who require no clinical monitoring in transit | No clinical observation during travel, so any change in condition depends on the patient or family to recognize |
Hospitals that base this decision on clinical acuity rather than cost tend to make more consistent choices. An RN-accompanied flight is an alternative to a dedicated air ambulance for patients who do not require that level of care. It is not a substitute for transport that requires critical care.
For a free quote on RN-accompanied commercial travel, call (210)-901-5226. Our team can review the patient's stability for travel and outline the escort scope before any booking is made.
Frequently Asked Questions
What does a hospital patient transfer medical escort include?
An RN escort accompanies the patient on the transfer, monitors condition during travel, follows the agreed care plan, and documents findings for the receiving team. The scope is set in advance according to the patient's clinical needs and the transfer route.
How does an escort help reduce readmission risk?
An escort reduces information loss at handoff points, supports confirmation that the receiving team is ready, and records observed changes during transit. Transitional care research indicates that structured transition support can reduce readmission rates, although results vary by study population and the timing of outcome measurement.
Is an RN escort the same as an air ambulance?
No. An RN escort accompanies the patient on a scheduled commercial airline flight and serves patients who are stable for travel but need supervision. Patients who require critical care during transport should be moved by a service designed for that level of care.
Who usually arranges a medical escort for a hospital transfer?
Discharge planners, case managers, hospitals, nursing homes, and families commonly arrange escorts. The sending facility confirms clinical readiness and provides the medical records, while the escort provider coordinates travel and the escort itself.
Will Medicare cover the cost of an escort?
Medicare's published guidance on ambulance services states that coverage extends to the nearest appropriate medical facility that can provide the care needed. That guidance does not address escorted commercial travel, so families should confirm coverage details with their insurer before booking.
How far in advance should a hospital transfer be planned?
Planning should begin as soon as a transfer is considered. The sending team, the receiving team, and the escort each need time to confirm acceptance, documentation, and travel arrangements, and early coordination reduces the risk of delays on the day of transfer.
We welcome feedback from hospital case managers, discharge planners, and families who have arranged escorted transfers, and we invite you to share which handoff steps made the greatest difference in your experience.
We would love your feedback and any insights you would share with others. What perspective would you add?